A Brain-Network Pattern May Signal Alzheimer’s Risk Before Symptoms
A Stanford-led study links resting brain connectivity to cognitive decline. It is a research signal, not a validated Alzheimer’s test.
On this page
A person can perform normally on a memory test while their brain’s activity patterns differ from those of peers. A study published in Science Advances on November 4 reports that one such pattern was associated with later cognitive decline and Alzheimer’s-related outcomes. The finding may help researchers ask when brain-network changes appear. It does not tell an asymptomatic person that they have Alzheimer’s or provide a test they can take today.
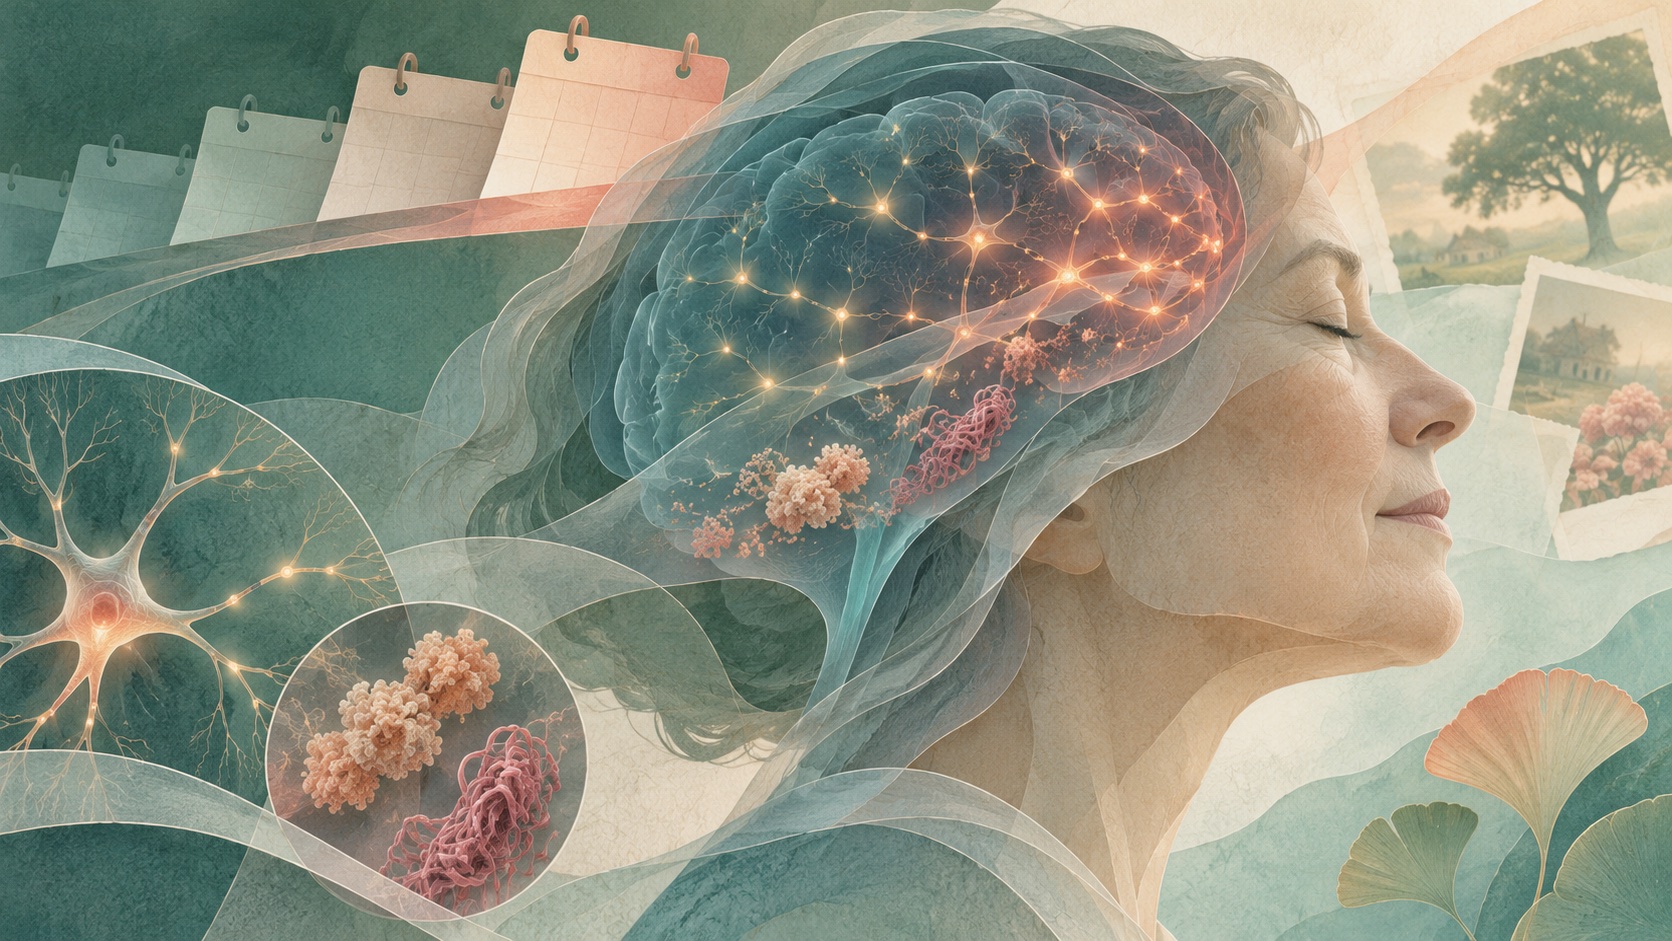
The researchers developed an Alzheimer’s Resilience-Vulnerability Connectome score, or ARC, from resting-state functional MRI. They first contrasted adults aged 75 and older at two ends of the cognitive spectrum: people with Alzheimer’s disease and “SuperAgers,” whose memory performance is unusually strong for their age. They then used the pattern to classify cognitively unimpaired adults into more SuperAger-like and more Alzheimer’s-like groups and examined outcomes over time. [1] [2]
The study reports 818 adults in a discovery group and 497 in a replication group. Within those groups, people assigned a more Alzheimer’s-like pattern showed faster subsequent cognitive decline, greater amyloid-beta accumulation and a higher likelihood of later Alzheimer’s diagnosis than those with a more SuperAger-like pattern. The authors report that the groups began with comparable cognition. These are associations across research cohorts, not proof that the brain pattern causes later decline. [1]
Why study function as well as plaques?
Alzheimer’s research often measures biological markers such as amyloid and tau, or observable performance such as memory scores. Functional connectivity looks at how brain regions’ signals vary together while the brain is at rest. It offers another way to describe brain organization, one that could potentially reflect vulnerability or resilience before a person notices symptoms.
The study’s design is notable because it does not simply compare a cognitively unimpaired person with an average. Instead, it uses contrasting groups to define patterns associated with exceptional preservation and diagnosed disease, then asks where other adults fall along that range. The aim is a more nuanced picture of cognitive aging, where people with similar baseline test scores could still have different underlying trajectories.
That framing also creates a validation challenge. The score depends on how the contrast groups are selected, how MRI data are processed, and how well the signal generalizes to people with different demographics, health histories and scanner environments. A pattern that separates two selected groups may be less precise when used to estimate risk for an individual in ordinary clinical care.
The study is observational. If early disease processes influence both connectivity and later decline, the association does not show that connectivity itself is the cause. Nor does a statistically predictive score tell researchers whether acting on it can change a person’s outcome. The study’s authors describe the work as potential early risk stratification; clinical usefulness would require external validation, agreed thresholds and evidence that the result improves decisions. [1]
Promising markers are not yet screening tools
This distinction is especially important when a finding concerns people without symptoms. The Alzheimer’s Association’s diagnostic criteria say current biomarker use is intended for evaluating symptomatic individuals, not cognitively unimpaired people, and recommend against diagnostic testing of unimpaired people outside research studies. The Association also notes that a potential biomarker needs validation across multiple, diverse groups before clinical use. [3] [4]
That is not a dismissal of the research. Earlier signals can help scientists design studies, identify groups for follow-up and understand how aging trajectories differ. It is a reminder that a cohort-level association and a clinical answer are different things. A research score does not yet provide a personal probability, a treatment choice or a reason to seek imaging.
The useful next questions are methodological: can independent teams reproduce the ARC pattern; does it add information beyond established markers and risk factors in diverse populations; how stable is the measurement across scanners and repeated visits; and does it help predict outcomes in a way that changes care? Answering those questions takes larger validation studies and careful prospective evaluation.
For now, the study broadens the scientific view of Alzheimer’s risk from plaques, proteins and memory tests to patterns of coordinated brain activity. Its contribution is a testable research signal. Until it is validated for clinical practice, it belongs in research conversations—not as a diagnosis for people who feel well.
Frequently asked questions
Can the new brain activity score diagnose Alzheimer’s disease?
No. The study describes an exploratory research score based on resting-state brain connectivity and associations with later outcomes. It has not been established as a clinical diagnostic or screening test.
What did the study measure?
Researchers derived a pattern from resting-state functional MRI by comparing groups of SuperAgers and people with Alzheimer’s disease, then studied how the pattern related to outcomes in cognitively unimpaired adults. The authors report discovery and replication cohorts, but further validation is needed before clinical use.
Should an asymptomatic person request an Alzheimer’s test because of this study?
The study does not provide a clinical test or individual risk estimate. Alzheimer’s Association criteria recommend against diagnostic biomarker testing in cognitively unimpaired people outside research studies. People with health concerns should discuss them with a qualified clinician.
Sources & further reading
- Science Advances: A functional connectome identifies vulnerability to cognitive decline and Alzheimer’s disease progression
- Stanford Medicine: Brain activity patterns may predict Alzheimer’s years before memory slips (November 4, 2026)
- Alzheimer’s Association: Criteria for diagnosis and staging of Alzheimer’s disease
- Alzheimer’s Association: Earlier diagnosis and biomarker validation
Keep reading
Quantinuum’s Nexus Roadmap Moves Quantum Work Up a Layer
Quantinuum’s Nexus roadmap adds quantum error-correction automation through 2029. What developers can use now and what remains planned.
AI Found an Antimicrobial Candidate. The Crucial Experiment Comes Next
A protein-function search can help prioritize a research candidate, but prediction and laboratory validation remain different stages.
AI Helped Fill a Missing Map of the Sky. Those Gaps Still Matter
A more complete ultraviolet sky map combines observations, calibration and statistical inference, each of which deserves a visible label.
/* Comments */
Comments are offline right now — we reconnect automatically, nothing is lost.